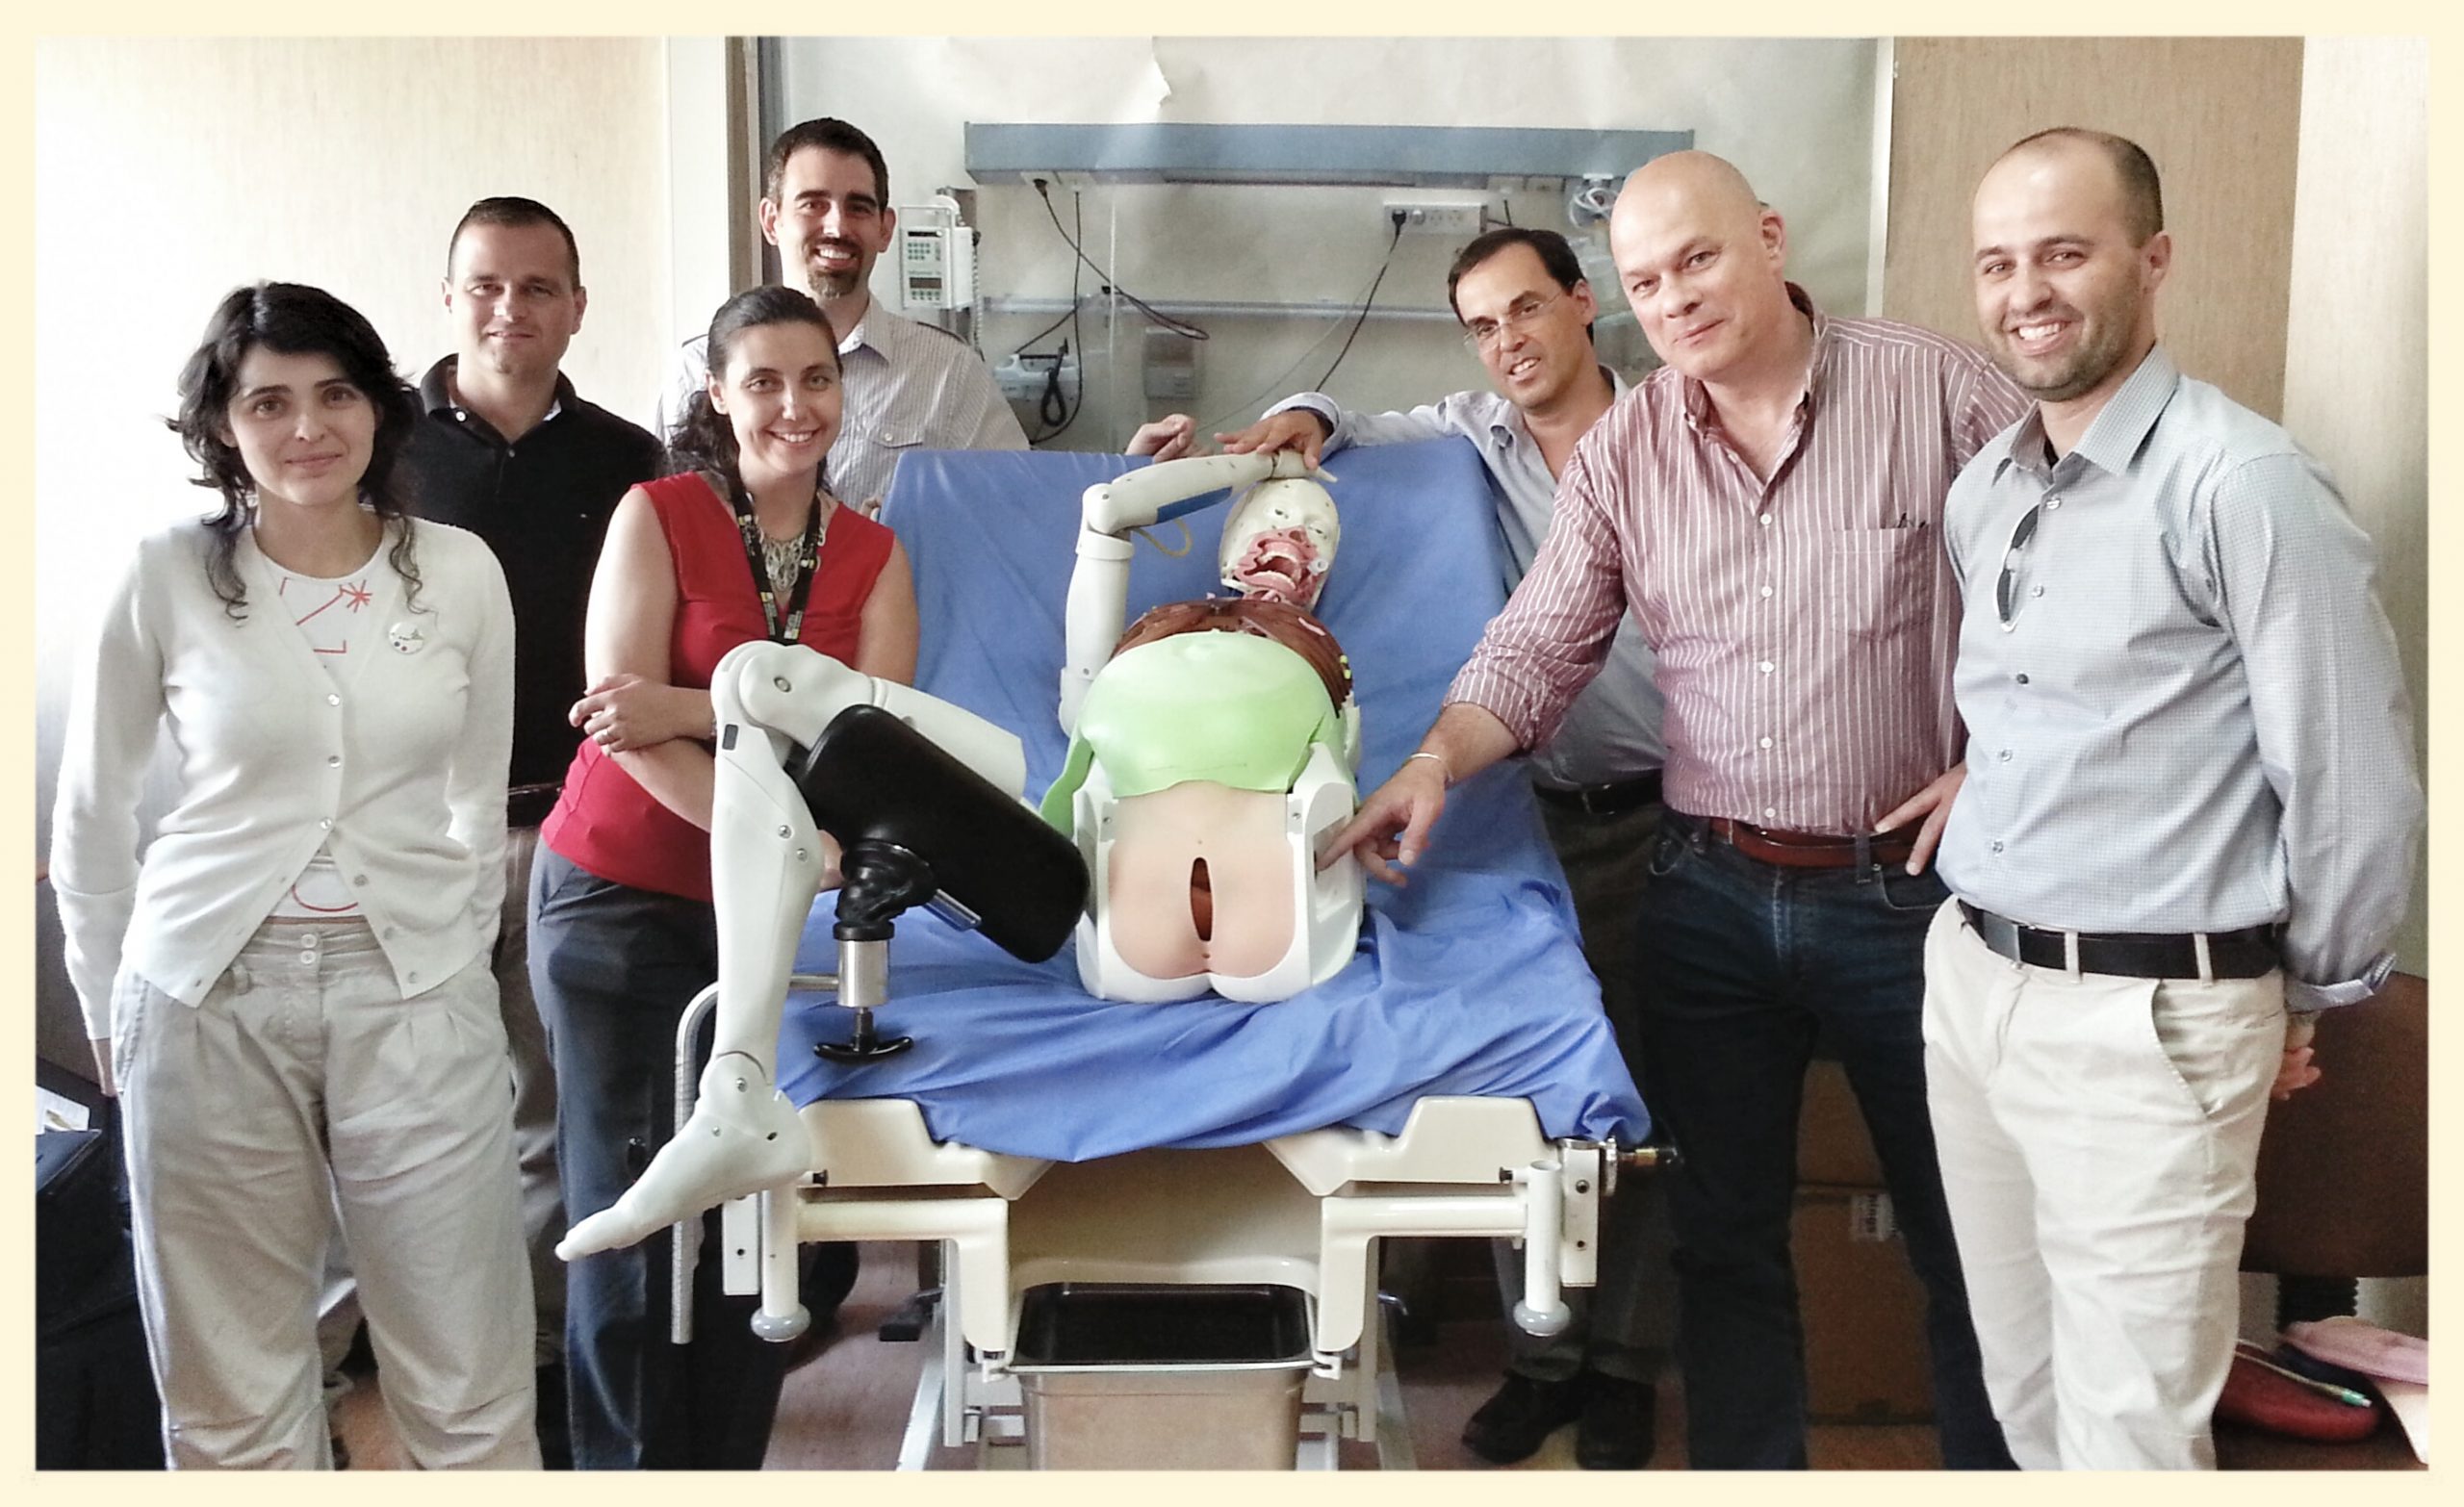
In-situ simulation is how hospitals build institutional competence for HALO procedures, the rare, time-critical interventions where individual skill alone is not enough. This article explores how simulation stress-tests clinical governance, training, readiness, and pathways, turning rare emergencies into rehearsed, predictable events rather than unprepared ones.
It is 3 a.m. A polytrauma patient rolls through the doors. The face is shattered, the airway swelling by the second. Laryngoscopy fails. Bag-mask ventilation fails. The saturation monitor starts its descent, and there is no plan B left, only a scalpel, a finger, a bougie, and a surgical front-of-neck access that someone in this room now has to perform in the next sixty seconds, correctly, the first time. In that instant, everything that determines whether the patient lives comes down to one uncomfortable question: is this hospital actually ready, or just hoping it is?
That question sits at the heart of a concept we recently proposed in the Journal of Trauma and Acute Care Surgery: institutional competence. We argued that for HALO (High Acuity, Low Occurrence) procedures, those rare, high-stakes, time-critical interventions like resuscitative thoracotomy, REBOA, or perimortem cesarean section, individual skill is necessary but never sufficient. A brilliant pair of hands, working inside a hospital with no protocol, no trained team, no blood on the shelf and no plan for what happens after the procedure, is not an asset. It is a liability waiting to happen.
If institutional competence is the destination, simulation is how you get there. This is not a minor footnote to our argument; it is arguably its engine room.
Why rarity breaks the old rules
HALO procedures are, by definition, procedures nobody does often enough. A recent Delphi survey of EMS physicians confirmed just how broad and how genuinely rare this category is, spanning cricothyrotomy, resuscitative hysterotomy, shoulder dystocia, junctional tourniquet application, and more. Most clinicians will encounter many of these only a handful of times in their careers, if ever. Traditional medical training assumes repetition builds competence. HALO procedures break that assumption at its foundation.
You cannot wait for clinical volume to build a skill that, by design, almost never shows up. And you certainly cannot wait for volume to build an institution’s readiness. This is where simulation stops being a nice educational add-on and becomes something closer to a survival strategy.
Simulation as the missing volume
Think of simulation as a way of manufacturing the experience that reality refuses to provide. A recent review on simulation for HALO trauma events laid out the toolkit beautifully: task trainers for psychomotor drilling, in-situ simulation for rehearsing inside the real clinical space with the real team, and virtual reality for scalable, repeatable, psychologically safe practice. Each modality answers a slightly different question, but together they answer the one that matters most: how do we get good, and stay good, at something we almost never do?
This is exactly the mechanism our framework needs. We wrote that individual skill, the technical micro-skills and split-second judgment required to execute a HALO procedure, is bounded and transferable. Simulation is precisely the tool that builds and maintains that boundedness. Mastery learning programs for emergency department thoracotomy, for example, have shown that none of the trainees met the passing standard at baseline, yet all did so after deliberate, simulation-based practice. That is not a training statistic. That is proof that competence for these procedures can be deliberately manufactured rather than accumulated by chance.
But simulation does something bigger
Here is where our institutional competence framework pushes the conversation further. Simulation is not only about producing a skilled individual. Done well, it is one of the few tools capable of rehearsing the institution itself.
Consider in-situ simulation. When a multidisciplinary team runs a HALO scenario within their own emergency department, using their own kits, storage, and corridors, they are not just polishing hand skills. They are stress-testing the system: is the kit where everyone thinks it is? Does the overhead call actually reach the right people in the right order? Does the pathway to the ICU or the OR actually exist, or does it live only on paper? In-situ simulation routinely uncovers latent safety threats, the equipment that is missing, the ambiguous role, the phone number nobody dials correctly under pressure, precisely the organizational fault lines that separate a competent institution from a collection of competent individuals.
This is institutional competence in action. Our framework names five domains that must work together: clinical governance, training and skill maintenance, readiness engineering, downstream pathway integration, and continuous quality learning. Simulation, especially in situ simulation, is one of the very few activities that can engage all five domains in a single afternoon. A single well-designed scenario can test whether the protocol is followed, whether the kit is ready, whether the handover to definitive care works, and whether the debriefing afterward actually changes anything.
That last point matters more than people realize. Because HALO events are rare, every real case and every simulated one becomes precious data. A structured debriefing after simulation, or after the rare real event, is what closes the loop, feeding lessons back into training, into equipment layout, into protocols. This reciprocal cycle, case in, learning out, is exactly how institutions compensate for rarity. Regional programs that paired simulation with structured post-case review have shown dramatic reductions in time to critical interventions, evidence that this loop is not theoretical, it works.
From skilled hands to a ready system
None of this diminishes the individual operator. Quite the opposite: simulation is what allows individual skill to reach the bar our framework demands in the first place, especially given how rarely these hands get to practice on real patients. But our central claim stands: a skilled operator inside an unready institution is a risk, not a solution.
The uncomfortable implication is that if an institution cannot commit to running realistic simulation, in the classroom and especially at the bedside, it may need to be honest about whether it can truly claim readiness for these procedures at all. Building institutional competence is not a one-time investment. It has to be sustained, rehearsed, and continuously questioned. Simulation is how we ask the question before reality forces the answer.
So the next time someone asks why a hospital invests time and money in scenarios that “probably won’t happen this year,” the answer is simple. It is not about the 99 simulations in which nothing goes wrong. It is about being ready for the one moment, at 3 a.m., when an airway closes, and someone has to cut, and everyone in the room already knows exactly what to do.
1. Colonetti E, Bonsano M, Carenzo L, Migliari M, Chiara O, Scalea T, Henry S. Individual skill and institutional competence: A framework for HALO procedure implementation. J Trauma Acute Care Surg. doi:10.1097/TA.0000000000005144
2. Hack KE, Levy MJ, Garfinkel E, Margolis AM. Establishing consensus-based high-acuity low-occurrence skills for EMS physicians: A pilot survey of EMS fellowship faculty. AEM Educ Train. 2022;6:e10828.
3. Culhane A, Rentz M, Yang T, Bailey L. From theory to practice: utilizing simulation for high acuity, low occurrence trauma events. Curr Emerg Hosp Med Rep. 2024;12(4):152-158.
READ ALSO